By tracking how the heart moves instead of just how much blood it pumps, a new deep learning model has mapped the hidden genetic drivers of a notoriously untreatable form of heart failure.
For decades, cardiologists have relied on a single metric to judge heart health: ejection fraction. If the heart pumps out a normal percentage of blood, it is deemed healthy, even when the patient is dying of heart failure. This diagnostic blind spot leaves millions of patients with heart failure with preserved ejection fraction (HFpEF) without effective therapies.
A new preprint from Stanford researchers challenges this crude binary measurement. By using computer vision to analyze the actual physical motion of the heart muscle, the study reveals that “preserved” function is an illusion. The AI exposes microscopic stutters in how the heart relaxes, linking these physical movements directly to specific genetic defects.
Tracking the silent stutters
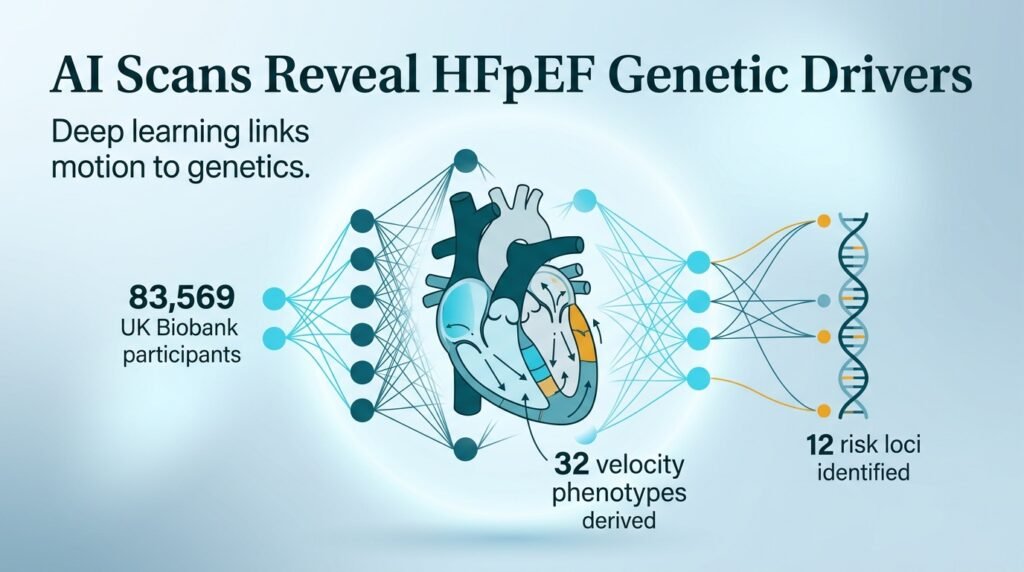
The researchers built a deep learning framework that combines image segmentation with optical flow analysis. They applied this tool to cardiac magnetic resonance images from 83,569 UK Biobank participants. The AI mapped 32 distinct velocity phenotypes across the entire cardiac cycle, capturing subtle mid-diastolic movements that humans cannot reliably measure.
The AI’s measurements translated directly to clinical outcomes and genetic markers:
- Patients with faster systolic left ventricular velocity had a lower risk of death, with a hazard ratio of 0.61 (95% CI 0.45-0.82).
- The genomic analysis mapped these precise movement patterns to 12 distinct risk loci.
- The SOX5 gene linked exclusively to mid-diastolic relaxation, while RABGAP1L showed a causal effect of -0.255 on early diastolic velocity (p = 5.49 x 10^-22).
Mapping the genetic culprits
This is not just a diagnostic tool; it is a gene-hunting machine. The PLN gene, which regulates calcium in the heart, showed the broadest impact across all phases of the heartbeat. This suggests that calcium handling is a central driver of how the heart relaxes and contracts.
Other genes showed highly specific roles. The SOX5 gene, which is involved in extracellular matrix development, seems to control the physical stiffness of the heart during its resting phase. This division of labor suggests that different patients suffer from different mechanical failures at the molecular level.
The analytical takeaway
The study has clear limitations, notably its reliance on the UK Biobank, which skews heavily toward healthier, white populations. Additionally, these findings come from a preprint and require clinical validation before they can guide treatment.
Even with these caveats, the implications are profound. For years, drug trials for HFpEF have failed because they treated all patients the same. This AI-driven phenotyping proves that diastolic dysfunction is not a single disease, but a collection of distinct mechanical failures driven by calcium handling and tissue remodeling. Drug developers now have precise genetic targets to shoot for.
Read the full study in medRxiv.