Yusuf Yesil, MD, MIS
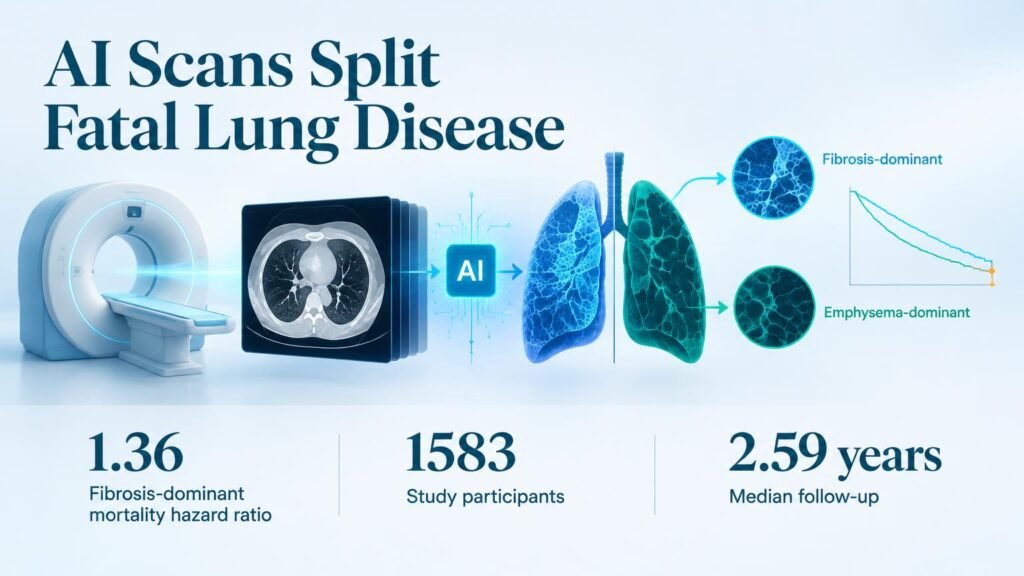
Clinicians treating combined pulmonary fibrosis and emphysema (CPFE) have long struggled to predict which patients will deteriorate rapidly. Standard visual readings fail to objectively pinpoint whether fibrosis or emphysema drives a patient’s pathology, leaving prognosis largely to guesswork. By replacing eye-balling with algorithmic segmentation, automated software introduces objective phenotyping directly into the diagnostic workflow.
That shift changes how we interpret CPFE severity.
A secondary analysis of prospective trial data published in Radiology reveals that structural dominance dictates survival. Researchers evaluated 1,583 participants (median age 65 years; 1,186 men) enrolled across the China Interstitial Lung Disease Collaboration Network between 2017 and 2024. A commercial AI workstation segmented high-resolution CT scans to compare total fibrosis against emphysema volume, categorizing patients into two distinct subgroups.
The algorithmic split was nearly even, but outcomes diverged sharply.
Fibrosis Drives Mortality Risk
Automated quantification stratified the cohort into 823 patients (52%) with fibrosis-dominant disease and 760 patients (48%) with emphysema-dominant disease. The fibrosis-dominant group presented with a median fibrosis load of 18% compared to 10% in the emphysema-dominant group (P < .001). Conversely, the emphysema-dominant cohort held a higher median emphysema load of 7% versus 6% (P < .001).
Over a median follow-up of 2.59 years, researchers recorded 513 deaths. The automated metrics linked tissue scarring directly to survival outcomes:
- Fibrosis-dominant disease carried a 36% higher risk of all-cause mortality after multi-variable adjustment (HR 1.36 [95% CI: 1.13, 1.62]; P < .001).
- Quantitative imaging successfully separated distinct clinical trajectories without relying on subjective reader scoring.
These findings build on earlier efforts to establish quantitative CT evaluation in CPFE. Previous studies established that CT scans offer prognostic value in complex lung disease, but automated phenotyping elevates those observations into reproducible risk strata.
Validation Remains the Final Barrier
The practical implication for pulmonologists is immediate: patients with predominant fibrosis demand aggressive monitoring and early anti-fibrotic intervention. However, the study carries important limitations. The cohort was predominantly male, reflecting regional referral patterns, and the trial relied on a single commercial AI software package. Algorithms trained on different software setups or lower-resolution scans may yield different cutoff values.
Quantifying CT metrics provides clear prognostic risk scores, but diagnostic precision alone does not equal therapeutic efficacy. Until prospective trials prove that routing patients to specific drugs based on AI phenotyping improves survival, software remains a powerful stratification tool rather than a standalone clinical cure.
Read the full study in Radiology.