A new AI model shows that complex real-time operating room data might be entirely optional for predicting post-surgery complications.
Engineers love complexity. They assume that feeding an AI every heartbeat and blood pressure fluctuation from a five-hour heart surgery will yield the sharpest ICU predictions.
A new study on cardiothoracic surgery complications upends this assumption. It turns out that simple, static medical records predict post-operative disasters just as well as high-frequency operating room feeds.
That redundancy is the real story.
Researchers built an ensemble model called PhysioFusion to predict adverse events in the ICU. They combined static patient data from the Society of Thoracic Surgeons database with real-time intraoperative time-series data. The model used neural networks, XGBoost, and support vector machines to process the inputs.
How the model performed
The combined model achieved strong overall metrics. It proved highly reliable at ruling out complications, though it flagged many false positives. Here is how the numbers stacked up:
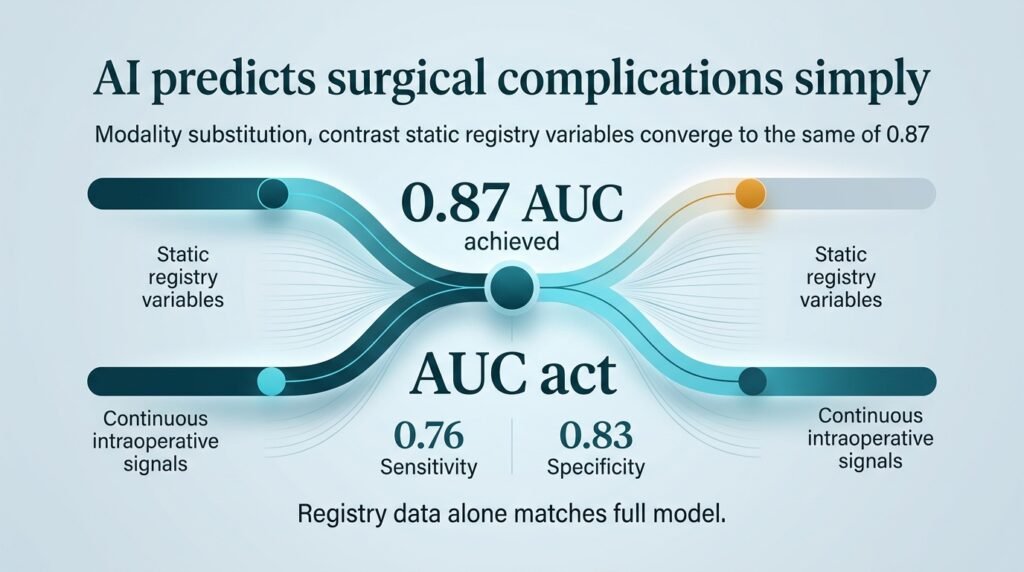
- An Area Under the Curve (AUC) of 0.87.
- A sensitivity of 0.76 and specificity of 0.83.
- A negative predictive value (NPV) of 0.96, alongside a positive predictive value (PPV) of 0.40.
- Key predictors included preoperative heart failure, intra-aortic balloon pump insertion, cardiopulmonary bypass duration, and white blood cell count.
The simplicity surprise
The real revelation lies in the ablation tests. When researchers trained the pipeline on static registry data alone, it achieved the exact same AUC of 0.87. Using only the intraoperative signals yielded an AUC of 0.83.
The two data types are substitutes, not complements.
This challenges the industry push toward hyper-complex, real-time data integration. If static preoperative charts do the heavy lifting, hospitals do not need to build expensive, low-latency data pipelines to benefit from predictive AI. Smaller clinics with basic registries can achieve the same predictive power as elite academic medical centers.
The road ahead
The study does have limits. It relies on retrospective data, and the low positive predictive value of 0.40 means clinicians will still face false alarms. Furthermore, while no single monitoring channel was load-bearing, mean arterial pressure and central venous pressure were the least substitutable.
Even so, the message is clear. Before spending millions on real-time data infrastructure, healthcare systems should look at the data they already have sitting in their registries.
Read the full study on medRxiv.