Pulling plastic stents too early after a liver transplant risks stricture recurrence, but leaving them in too long adds unnecessary endoscopic procedures.
A static 12-month rule for endoscopic biliary stenting is a blunt instrument. While biliary strictures remain a common complication in living-donor liver transplantation (LDLT), clinical practice has relied heavily on broad timelines rather than individual biological risk. A new study shows machine learning can spot which patients are safe for earlier removal and which need extended surveillance.
The core tension in post-transplant care is balancing tissue healing against patient strain. Endoscopic retrograde biliary drainage (ERBD) fixes anastomotic strictures, yet doctors lack precise markers for when the duct is stable. By shifting from fixed calendar dates to continuous risk scoring, algorithms can help teams avoid both premature stent pulls and excess endoscopies.
Predicting stricture recurrence with clinical data
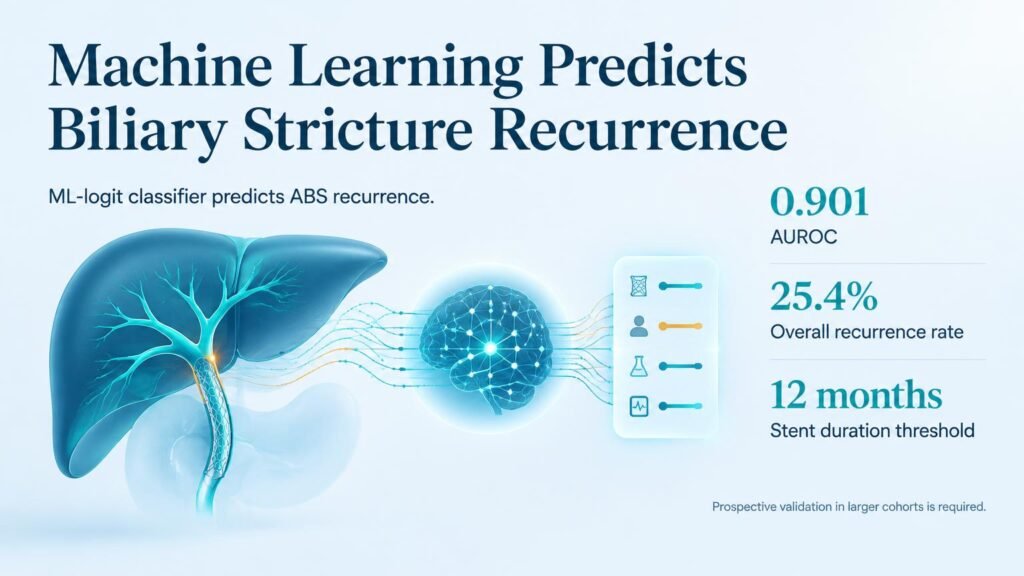
Researchers tracked 173 patients across three tertiary centers who had ERBD stents removed for anastomotic biliary strictures. The cohort was split into an internal group of 131 patients and a external validation group of 42 patients. Overall, strictures recurred in 25.4% of patients, with a median recurrence time of 297 days.
Statistical analysis identified key drivers of failure. Patients facing higher risk had shorter stent durations (HR 3.45), higher total ERCP procedure counts (HR 2.12), elevated bilirubin (HR 2.58), and elevated alkaline phosphatase (HR 2.21) at the time of removal. Keeping stents in for more than 12 months cut the recurrence rate from 47.1% down to 10.7%.
Machine learning outperforms fixed timelines
To move beyond arbitrary cutoffs, the team built a logistic regression classifier incorporating stent duration, ERCP count, and lab values. The model hit an area under the curve (AUROC) of 0.901. That significantly beat standard 12-month thresholds (AUROC 0.688) and 396-day targets (AUROC 0.730).
That performance gap matters for post-transplant management.
When stratified by the algorithm, low-risk patients achieved a 5-year recurrence-free survival rate of 83.4%. High-risk patients plummeted to 11.4% (HR 9.06). This risk separation builds on historical work showing that maximal stent therapy achieves long-term duct patency, but offers a far more granular exit strategy.
Retrospective limits require prospective testing
The findings come with clear caveats. The model demonstrated limited sensitivity in the small external validation cohort of 42 patients. Because this was a retrospective study, selection bias could skew the biochemical baseline.
Retrospective accuracy does not guarantee patient benefits. Hepatology teams should not shorten stent durations based solely on this tool today. However, the data proves that combining routine liver panels with procedure history predicts duct failure better than the calendar alone. Prospective multi-center trials are the mandatory next step.
Read the original research in the International Journal of Surgery.