 Yusuf Yesil, MD, MIS
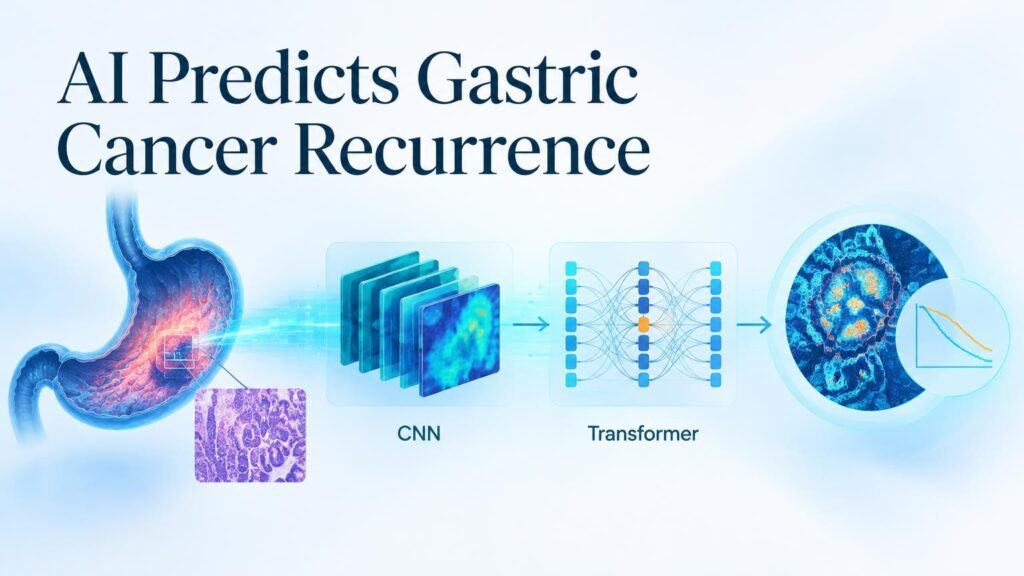
Biopsies miss crucial spatial immune markers because they sample only a fraction of a tumor. Tertiary lymphoid structures—aggregates of immune cells that signal a strong anti-tumor response—are vital prognostic indicators, but measuring their maturation historically required invasive, tissue-biased sampling.
That diagnostic gap leaves oncologists guessing which patients face high recurrence risks after surgery. This new study shows non-invasive imaging analysis can bridge that gap.
Mapping Immune Response Non-Invasively
Researchers built CTransNet, a multitask hybrid model combining a ResNet50 convolutional neural network with a Transformer. The tool predicts tertiary lymphoid structure maturation and peritoneal recurrence-free survival directly from radiological scans.
The retrospective study leveraged eight Chinese patient cohorts recruited between Jan 1, 2005, and Feb 28, 2022 across four major medical centers: Nanfang Hospital, Sun Yat-sen University Cancer Center, Yunnan Cancer Hospital, and Guangdong Provincial Hospital of Chinese Medicine.
Histological tissue samples classified patients into three distinct categories: TLS0 (absent), TLS1 (immature primary follicle-like), and TLS2 (mature secondary follicle-like with germinal centers). CTransNet learned to identify these underlying immune microenvironments directly from pre-operative imaging.
Strong Classification and Survival Stratification
In the training cohort, CTransNet achieved exceptional diagnostic accuracy across all tertiary lymphoid structure stages:
- TLS0 classification area under the ROC curve: 0.910 (95% CI 0.882-0.938).
- TLS1 classification AUC: 0.925 (95% CI 0.899-0.951).
- TLS2 classification AUC: 0.953 (95% CI 0.933-0.974).
- Peritoneal recurrence-free survival prediction concordance index: 0.654 (95% CI 0.620-0.688).
Across all validation cohorts, patients assigned low model scores experienced significantly higher 5-year peritoneal recurrence rates of 66.69% compared to 26.28% for high-score patients in the training cohort (p<0.0001). Multivariate analysis confirmed score-based risk stratification served as an independent predictor of peritoneal recurrence-free survival, disease-free survival, and overall survival.
Directing Systemic Therapy Selection
The clinical value extends beyond pure prognosis to therapy selection. For patients with stage II or III disease, adjuvant chemotherapy significantly improved disease-free and overall survival in low-score patients, but provided no significant benefit to high-score patients.
The model also predicted immunotherapy outcomes across two independent cohorts receiving anti-PD-1 or anti-PD-L1 inhibitors for at least two cycles. High-score patients achieved objective response rates of 54.5% vs 5.6% in immunotherapy cohort 1 (p<0.0001) and 53.1% vs 9.7% in cohort 2 (p=0.0010).
These figures challenge the assumption that all post-surgical stage II/III patients require aggressive chemotherapy. High-score patients might safely forgo toxic regimen toxicity while focusing on targeted immunotherapy.
Translational Limitations
High classification AUCs do not automatically equal clinical adoption. The model’s predictive C-index for survival remains modest at 0.654, demonstrating that imaging features only capture a portion of recurrence risk dynamics.
Furthermore, all eight cohorts were retrospective and exclusively derived from Chinese hospitals. Prospective prospective global trials are required before CTransNet can replace invasive pathology or redefine clinical treatment guidelines.
Read the full study in The Lancet Digital Health.


